

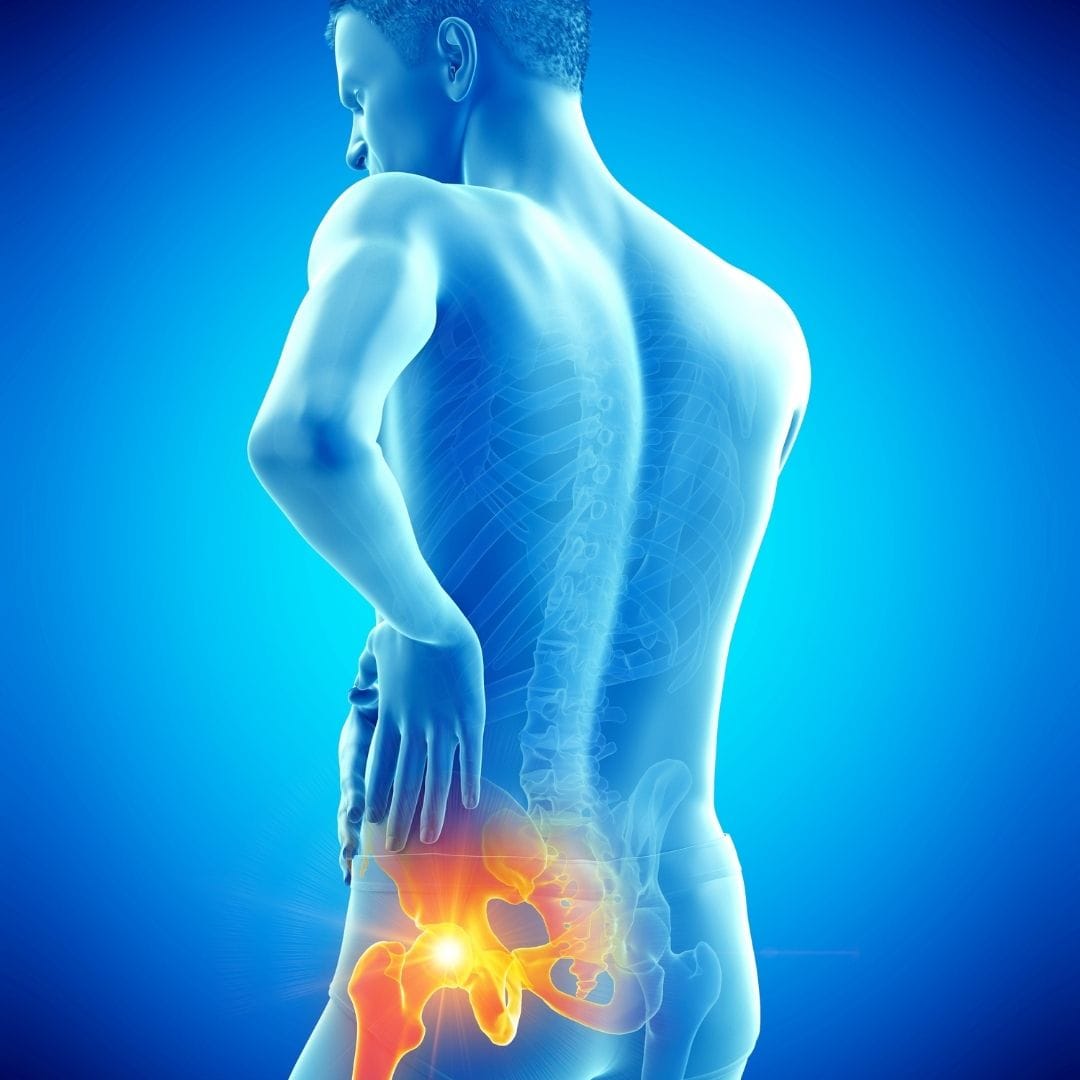
When a 32-year-old presents with persistent groin pain that started gradually, worsens with sitting for long periods, and catches sharply when crossing the legs or getting out of a car — the diagnosis is rarely what they expect. Most assume hip problems are something that happens to older people. The reality is that hip pain in young adults has its own set of causes, entirely separate from the osteoarthritis that affects older patients, and getting the right diagnosis early makes a significant difference to outcomes.
Hyderabad's working population — long desk hours, desk-to-car-to-desk commutes, weekend sport — creates a specific set of hip pain patterns that are increasingly common at Pure Ortho Hospitals, Sainikpuri. Understanding what is actually causing the pain is the first step to addressing it.
The Causes Are Different in Young Adults
Hip pain in someone over 60 is most commonly osteoarthritis — cartilage wear accumulated over decades. In someone under 45, osteoarthritis is rarely the primary cause. The conditions causing hip pain in younger patients are structural, mechanical, or circulatory — and they need to be correctly identified because the treatment for each is completely different.
Femoroacetabular Impingement (FAI)
Abnormal bone shape at the hip joint causing painful impingement during movement. The most common structural cause of groin pain in active young adults. Often present for years before diagnosis. Causes labral damage if untreated.
Hip Labral Tear
Tear of the cartilage ring around the hip socket. Causes deep groin pain, clicking, and catching. Often occurs alongside FAI. Confirmed on MRI arthrogram. Managed with physiotherapy or hip arthroscopy.
Avascular Necrosis (AVN)
Death of femoral head bone from disrupted blood supply. Increasingly common post-COVID in patients who received steroids. Presents as groin pain that worsens with weight-bearing. X-ray normal early — requires MRI for diagnosis. Time-critical.
Hip Flexor Tendinopathy
Degeneration or inflammation of the iliopsoas or rectus femoris tendon at its hip attachment. Common in runners, cyclists, and desk workers. Causes groin and anterior hip pain. Responds well to structured physiotherapy.
Stress Fracture of the Femoral Neck
One of the most serious sports injuries — a crack in the upper femur from repetitive loading. Causes progressive groin pain in runners and military personnel. Requires immediate assessment — risk of complete fracture and AVN if missed.
Greater Trochanteric Pain Syndrome
Pain on the outer hip over the bony prominence. Caused by gluteal tendinopathy or trochanteric bursitis. Worsens with lying on the affected side and crossing legs. Common in women and runners. Responds to physiotherapy and injection.
Snapping Hip Syndrome
Audible or palpable snap around the hip with movement — from the IT band, iliopsoas tendon, or an intra-articular problem. Mostly benign when external. Intra-articular snapping (labral or cartilage) requires investigation.
Referred Pain from the Spine
L3-L4 nerve root compression from disc prolapse or stenosis can refer pain to the groin and anterior thigh — mimicking hip pathology exactly. A spine examination and imaging is essential when hip examination does not reproduce all the symptoms.
The Post-COVID AVN Problem — A Specific Concern for Young Adults in Hyderabad
Post-COVID Avascular Necrosis — Who Is at Risk
- Received corticosteroids (dexamethasone, methylprednisolone) during COVID-19 treatment
- Hip or groin pain developing 3 to 18 months after COVID treatment
- Pain in both hips — bilateral AVN is common in steroid-related cases
- Age 25-50 — post-COVID AVN is being seen in people far younger than typical AVN patients
- X-ray may be completely normal in early AVN — MRI is essential
- Joint-preserving treatment is only possible before the femoral head collapses — early diagnosis is critical
Post-COVID AVN has been documented in significant numbers across India since 2021. If you received steroids during COVID treatment and have developed hip or groin pain since — even mild, even intermittent — an MRI of both hips at Pure Ortho Hospitals, Sainikpuri will determine whether AVN is developing and whether the joint-preserving window is still open.
Symptoms — What Hip Pain Actually Feels Like
Deep Groin Pain
Pain felt deep in the groin rather than on the outer hip — the classic location for intra-articular hip problems including FAI, labral tears, and AVN
Pain Getting In and Out of Car
The movement required — hip flexion combined with rotation — directly loads the impingement zone and is a hallmark complaint of FAI and labral tears
Pain After Prolonged Sitting
Sitting holds the hip in flexion — sustained loading of an already compressed labrum or impingement zone produces stiffness and pain when standing
Clicking or Catching
A sharp click, catch, or giving way sensation in the hip — suggests labral involvement or snapping hip syndrome
Reduced Hip Rotation
Difficulty crossing legs, sitting cross-legged, or rotating the hip inward — common in FAI where the bony abnormality limits rotational range
Outer Hip Pain
Pain on the outer hip over the bony prominence — greater trochanteric pain syndrome from gluteal tendinopathy, worsened by lying on that side at night
Why Hip Pain Gets Diagnosed Late in Young Adults
Hip pain in young adults is frequently misdiagnosed or dismissed for several reasons. Patients are told they are "too young" for hip problems. Symptoms are attributed to muscle strain or sports injury without imaging. Standard X-rays may appear normal in FAI, early AVN, and labral tears — conditions that require MRI or MRI arthrogram for accurate diagnosis. Referred pain from the spine further confuses the picture.
The consequence of late diagnosis is significant. FAI with an untreated labral tear progresses to cartilage damage and early osteoarthritis. AVN caught after bone collapse has far fewer treatment options than AVN caught at Stage 1 or 2. Femoral neck stress fractures that are missed risk complete fracture — a surgical emergency.
Diagnosis — Getting It Right
Assessment at Pure Ortho Hospitals, Sainikpuri
- FADIR test — Flexion, Adduction, Internal Rotation — the primary clinical test for FAI and labral pathology. Positive when it reproduces the patient's groin pain.
- FABER test — Flexion, ABduction, External Rotation — assesses posterior labral and sacroiliac pathology
- X-ray — shows bony FAI morphology (cam or pincer deformity), joint space, and later AVN changes. Normal X-ray does not exclude early hip pathology.
- MRI — detects AVN from earliest stages, bone stress reactions, cartilage damage, and soft tissue pathology. Essential for any young adult with persistent hip pain and normal X-ray.
- MRI arthrogram — gadolinium injected into the hip joint before MRI significantly improves labral tear detection. The investigation of choice when labral pathology is suspected.
- Spine assessment — to exclude referred pain from L3-L4 nerve root compression when hip examination is not fully consistent with intra-articular pathology
Treatment — Depends Entirely on the Diagnosis
Treatment by condition at Pure Ortho Hospitals, Sainikpuri
- FAI without labral tear — physiotherapy focusing on hip strengthening and movement pattern retraining. Activity modification to reduce impingement loading. Intra-articular injection for pain management.
- FAI with labral tear — hip arthroscopy to reshape the impinging bone (femoroplasty/acetabuloplasty) and repair or reconstruct the labrum. Keyhole surgery, day case, return to sport 4-6 months.
- AVN — early stage — protected weight-bearing, eliminating causative factors, core decompression procedure to stimulate revascularisation. Time-critical — only available before bone collapse.
- AVN — late stage — hip replacement. At Pure Ortho Hospitals, robotic hip replacement under Dr. V.S. Abhilash Kumar S restores pain-free function with precise implant positioning.
- Hip flexor tendinopathy — structured physiotherapy, load management, progressive tendon loading programme. Injections for refractory cases.
- Greater trochanteric pain syndrome — gluteal strengthening physiotherapy, avoidance of hip adduction postures, corticosteroid injection for acute flares.
- Femoral neck stress fracture — immediate non-weight-bearing. Surgical fixation for high-risk fractures. MRI essential as X-ray may be normal.
Do Not Wait — See a Specialist If Your Hip Pain
- Has lasted more than 6 weeks without clear improvement
- Followed COVID steroid treatment — even if mild
- Is in a runner and worsening during training
- Involves clicking, catching, or giving way
- Radiates to the knee with no knee injury
Call Pure Ortho Hospitals, Sainikpuri: 8686868208
Meet the Specialists at Pure Ortho Hospitals
Dr. G. Uday Sekhar Reddy
MBBS, MS Ortho, MCh Ortho
Dr. V.S. Abhilash Kumar S
MBBS, MS Ortho, FIJR, FISS (S.Korea, USA) — Clinical Director
Dr. Pudari Manoj Kumar
MBBS, MS Ortho, FIJR, FIRJR
Dr. L. Sreeram
MPT (Ortho), FDOR, MIAP
Dr. L. Sri Dharani
BPT, MIAP, PTOTA (Canada)
Frequently Asked Questions
Other Departments at Pure Ortho Hospitals
Hip Pain Under 50 Deserves a Proper Diagnosis
Most causes of hip pain in young adults are treatable — but the window for joint-preserving treatment closes as conditions progress. Visit Pure Ortho Hospitals, Sainikpuri, Hyderabad for an MRI-based hip evaluation.
Call 8686868208More from Pure Ortho Hospitals
This article is for patient education only. Please consult a qualified orthopaedic surgeon before making any treatment decisions.