

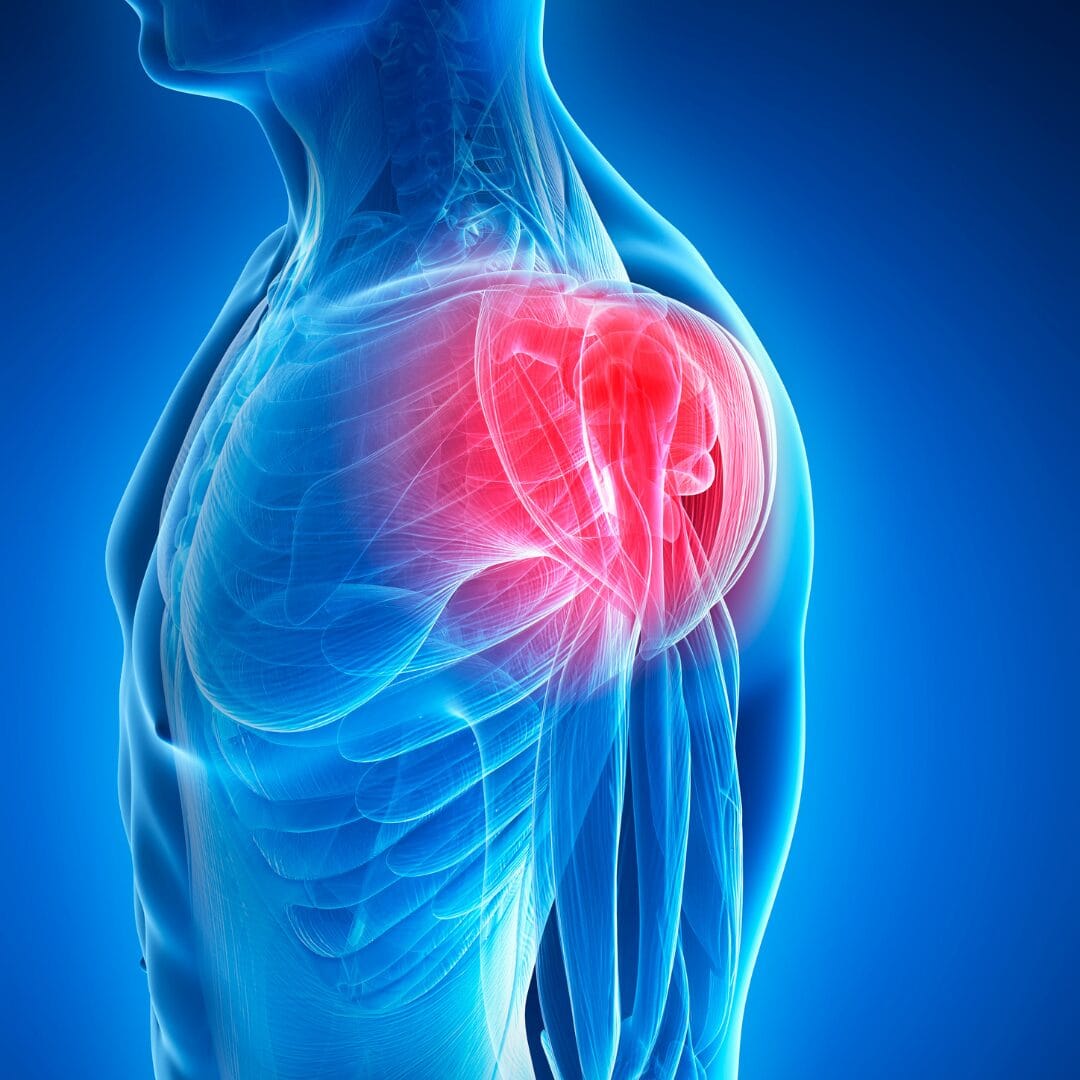
The shoulder is the most mobile joint in the body, and the rotator cuff is the reason it can be. Four muscles — supraspinatus, infraspinatus, teres minor, and subscapularis — form a cuff of tendons that surround the humeral head (the ball of the shoulder) and keep it centred while the arm moves. When any of these tendons tears, the mechanics of the entire shoulder are disrupted.
Rotator cuff tears are extremely common. Imaging studies show that roughly 25% of people over 60 have a rotator cuff tear — and many of them have no pain at all. This is a critical fact that gets lost in how the diagnosis is communicated. An MRI showing a tear does not automatically mean surgery. The decision is far more nuanced — and getting it right determines whether the outcome is good or whether the patient undergoes an operation they did not need, or avoids one they did.
The Four Muscles of the Rotator Cuff
- Supraspinatus — runs across the top of the shoulder; initiates arm elevation and is the most commonly torn tendon in rotator cuff injuries
- Infraspinatus — at the back of the shoulder; externally rotates the arm; the second most commonly torn
- Teres Minor — also at the back; assists external rotation and depression of the humeral head
- Subscapularis — at the front; the only internal rotator in the cuff; tears here produce specific weakness and instability
Most tears involve the supraspinatus, often at its insertion point on the greater tuberosity of the humerus — the area under highest mechanical load with the lowest blood supply.
Grades of Tear
Less than full thickness
Tendon is partially torn but still attached to the bone. Classified by which surface is involved (articular-side, bursal-side, or intratendinous) and what percentage of the tendon thickness is involved. Small partial tears often respond well to non-surgical treatment.
Complete through-and-through tear
The tendon is torn completely. Further classified by size: small (<1cm), medium (1–3cm), large (3–5cm). Full-thickness tears do not heal on their own. Active individuals generally benefit from surgical repair, particularly if they are under 65 and the tear is medium or large.
More than 5cm or involving 2+ tendons
Involves multiple tendons. The muscle may have retracted significantly and developed fatty infiltration (irreversible muscle wasting). These are the most technically demanding repairs. Advanced cases may not be repairable and require different surgical solutions.
Symptoms — What a Rotator Cuff Tear Feels Like
- Pain on the outer side of the shoulder or upper arm, often described as deep and aching
- Night pain — pain when lying on the affected shoulder, often disturbing sleep
- Painful arc — pain with lifting the arm between roughly 60 and 120 degrees of elevation
- Weakness lifting the arm sideways or forward, particularly against resistance
- Difficulty reaching behind the back or overhead
- In complete tears: a visible or palpable weakness, drop arm (inability to hold the arm elevated), or a clunking sensation
See a Specialist Urgently If
- Complete loss of shoulder strength following a fall, road accident, or dislocation — acute complete tear needs early repair
- Arm weakness progressing rapidly over days — nerve injury must be excluded
- Shoulder pain with fever or redness over the joint — septic arthritis is a surgical emergency
- Significant weakness in a young active patient after a single traumatic event — delay worsens outcome
The Surgery vs. No Surgery Decision
When Is Surgery the Right Answer?
Conservative Treatment First
- Small partial thickness tears
- Full thickness tears in older, less active patients (>65–70) with mild symptoms
- Incidental tear found on imaging with minimal pain
- Acute tear with no significant weakness — 6–12 weeks of physio first
- Tears in patients with significant medical comorbidities where surgical risk is high
- Patient preference for non-surgical management after informed discussion
Surgery Recommended
- Full thickness tears in active patients under 65 with functional demands
- Acute traumatic full thickness tear in a young or middle-aged patient
- Large or massive tears with significant weakness
- Partial thickness tear >50% of tendon thickness not responding to 3–6 months of physio
- Subscapularis tear (anterior instability risk)
- Failed conservative treatment after adequate time
Non-Surgical Treatment
Physiotherapy — The Foundation
Rotator cuff rehabilitation focuses on: strengthening the intact cuff muscles to compensate for the tear, periscapular strengthening (lower trapezius, serratus anterior) to stabilise the scapula, posterior capsule stretching to restore full range, and postural correction. A well-supervised programme over 12 weeks produces significant improvement in pain and function in the majority of partial and small full-thickness tears.
Subacromial Corticosteroid Injection
An injection into the subacromial space (the area between the rotator cuff and the overlying acromion bone) reduces bursitis and inflammation that accompanies most rotator cuff tears. Provides pain relief that allows physiotherapy to be more effective. Given under ultrasound guidance for accurate placement. Typically used early in the conservative treatment phase rather than as a standalone long-term treatment.
PRP Injection for Partial Tears
For partial thickness rotator cuff tears that have not responded to physiotherapy and corticosteroid injection, ultrasound-guided PRP (Platelet-Rich Plasma) injection into the tear site provides growth factor stimulation. Evidence is strongest for partial tears and tendinopathy. Not indicated for complete full-thickness tears where the structural defect needs repair, not biologic augmentation.
Arthroscopic Rotator Cuff Repair — How It Works
Arthroscopic (keyhole) rotator cuff repair is the standard surgical approach at Pure Ortho Hospitals. The surgeon uses a small camera (arthroscope) and specialised instruments inserted through 3–4 small portals around the shoulder. Under the arthroscope, the surgeon:
- Prepares the tear site — debrides the torn tendon edges and the bone footprint where the tendon will be reattached
- Places suture anchors — small screws embedded in the bone, each carrying sutures that will hold the tendon down
- Passes sutures through the torn tendon and ties them down to pull the tendon back to the bone
- Performs acromioplasty if needed — shaving the undersurface of the acromion to reduce impingement on the repaired tendon
The procedure is done under general anaesthesia combined with a nerve block (interscalene block) for post-operative pain control. Most patients go home the same day or the following morning.

Recovery Timeline After Surgery
Sling and Passive Motion
Arm in a sling to protect the repair. Passive physiotherapy — the therapist gently moves the arm through a limited range. Grip and elbow exercises to prevent stiffness. No active shoulder movement.
Active Assisted Motion
Sling is weaned off. The patient begins using the arm with assistance from the other hand or a pulley. Range of motion exercises within a progressively increasing arc.
Strengthening Begins
Light resistance exercises for the rotator cuff and periscapular muscles. The tendon is still maturing at this point — loads are kept within safe limits while strength is progressively rebuilt.
Return to Full Function (Small-Medium Tears)
Most patients with small or medium tears are functionally recovered by this point — able to return to desk work, driving, and light activity. Sport-specific rehabilitation begins.
Full Return (Large Tears, Sport, Manual Work)
Large and massive tear repairs take longer to mature. Return to overhead sport, heavy manual work, or high-demand activity is typically at 9–12 months. Final strength testing should confirm symmetry before full clearance.
Myths and Facts
"MRI shows a tear — I need surgery"
Rotator cuff tears are extremely common in adults over 50. Many are asymptomatic. The MRI finding must match the clinical symptoms, the patient's demands, and the tear characteristics before surgery is recommended.
The decision is clinical, not radiological
A surgeon assesses the tear grade, the patient's age, activity level, symptom severity, and response to conservative treatment — not the MRI alone.
"Rotator cuff tears heal on their own with rest"
Full thickness tears do not heal — the biology of tendon repair does not work across a complete structural gap. Rest reduces symptoms but does not repair the tear. Non-surgical treatment manages symptoms; it does not fix the anatomy.
Partial tears can improve; full thickness tears cannot self-heal
Small partial tears can become asymptomatic with appropriate physiotherapy. Complete tears require surgical repair if the functional deficit is significant and the patient is active.
"Waiting to have surgery makes no difference"
For full-thickness tears in active patients, prolonged delay allows the torn tendon to retract and the muscle to undergo fatty infiltration — changes that are permanent and make repair harder and less reliable.
Early repair in the right candidate gives the best outcome
When surgery is indicated — particularly in younger active patients with full-thickness tears — earlier repair produces better tendon quality, easier surgery, and more reliable results.
Our Shoulder Surgeons
Dr. V.S. Abhilash Kumar S
Dr. G. Uday Sekhar Reddy
Dr. Sai Krishna C.S
Dr. L. Sreeram
Frequently Asked Questions
Other Departments
Shoulder Pain or Weakness That Isn't Resolving?
A proper shoulder assessment — clinical examination and imaging — tells you exactly what is torn, how significant it is, and what the right treatment is. Book a consultation at Pure Ortho Hospitals, Sainikpuri, Hyderabad.
Call 8686868208More from Pure Ortho Hospitals
This article is for patient education only. Please consult a qualified specialist before making any treatment decisions.